
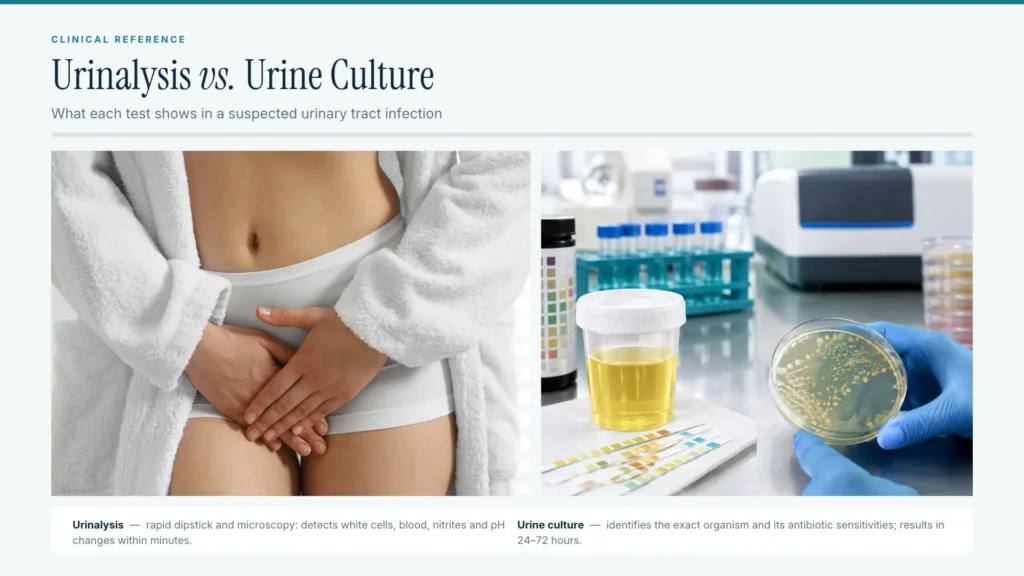
When a urinary tract infection is suspected, two laboratory tests are commonly ordered: the urinalysis and the urine culture. They are frequently confused, yet they answer different questions. One screens for signs of infection within minutes; the other identifies the organism and guides the choice of antibiotic.
Urinalysis: fast screening
A urinalysis combines a dipstick test with, where needed, microscopic examination of the urine. Two dipstick markers matter most for infection:
- Leukocyte esterase is an enzyme released by white blood cells. A positive result suggests pyuria, meaning inflammation in the urinary tract.
- Nitrite appears when certain bacteria, mainly Gram-negative rods such as Escherichia coli, convert nitrate in the urine to nitrite. A positive nitrite is fairly specific for bacteriuria, but a negative result does not exclude infection. Some organisms, including enterococci, do not produce nitrite, and urine that has spent little time in the bladder may test negative.
Microscopy can add a white cell count, bacteria and red cells. Many squamous epithelial cells point to contamination from skin during collection.
Urine culture: identification and susceptibility
For a culture, a measured volume of urine is spread on growth media and incubated. Results usually take 24 to 48 hours. The report states which organism grew, the colony count per millilitre and, after susceptibility testing, which antibiotics are likely to be effective.
The classic threshold for significant bacteriuria is 100,000 colony-forming units per millilitre in a clean-catch sample. Lower counts can still be meaningful in a patient with typical symptoms or in a sample taken by catheter. Growth of several different organisms usually indicates contamination rather than infection.
When is a culture needed?
In otherwise healthy, non-pregnant women with typical symptoms of an uncomplicated bladder infection, treatment is often started on the basis of symptoms and urinalysis alone. A culture is generally recommended when:
- the patient is male, pregnant or a child,
- there is fever, flank pain or other signs of kidney involvement,
- symptoms return shortly after treatment or infections are recurrent,
- the patient has a catheter, a urological abnormality or recent antibiotic exposure.
How these findings translate into treatment decisions, including short-course therapy and the role of local resistance, is covered in this review of how UTI treatment has evolved.
Collection decides the quality of the result
Both tests depend on a proper sample. The standard is a midstream clean-catch specimen: the first portion of urine is passed into the toilet, the middle portion is collected in a sterile container. The sample should reach the laboratory promptly or be refrigerated, because bacteria multiply at room temperature and can produce falsely high counts.
A positive culture is not always an infection
Bacteria in the urine of a person without symptoms are called asymptomatic bacteriuria. It is common in older adults and in people with catheters. Current guidelines advise against screening for or treating it in most groups, with pregnancy and certain urological procedures as the main exceptions. Laboratory results therefore have to be read together with symptoms, not in place of them.
This article is for general information and does not replace individual medical advice. Further clinical education topics are available at cme-ce.com.
